Key takeaways
- This page offers 25 free RCES practice questions with fully worked explanations, requiring no signup or payment.
- The questions are grouped into five blueprint-matched topics: EP anatomy and the conduction system, ECG and rhythm foundations, the diagnostic EP study and pacing protocols, access/ablation and 3D mapping, and devices (pacemakers, ICDs, and CRT).
- These are original questions written to the CCI RCES electrophysiology blueprint, not reproductions of real exam items.
- The Cardiac Codex app's full practice bank contains 2,198 questions with explanations, plus two full-length, live and timed RCES mock exams, flashcards, and an AI tutor called Cardiac Coach.
- A free 25-question RCES diagnostic that scores results by topic is also available.
EP anatomy & the conduction system
-
1To be formally classified as part of the specialized cardiac conduction system, myocytes must meet which classic anatomical criteria?
- AThey must be histologically discrete, traceable across serial histologic sections, and electrically insulated from adjacent working myocardium by fibrous tissue
- BThey must contract with greater force than working myocardium
- CThey must be visible on standard 12-lead ECG
- DThey must lack any gap junction expression
Correct answer: A — They must be histologically discrete, traceable across serial histologic sections, and electrically insulated from adjacent working myocardium by fibrous tissue
Classic criteria require conduction-system myocytes to be histologically discrete, traceable across serial sections, and electrically insulated from adjacent working myocardium by surrounding fibrous tissue.
-
2Electrophysiologically, the fibrous skeleton of the heart functions as which of the following?
- AA high-conductivity pathway that accelerates AV conduction
- BA structure with no electrophysiological role
- CAn electrically impermeable 'firewall' that isolates atrial from ventricular electrical activity
- DA secondary pacemaker site
Correct answer: C — An electrically impermeable 'firewall' that isolates atrial from ventricular electrical activity
The fibrous skeleton, composed of non-conducting collagen and elastic fibers, serves as an electrically impermeable firewall isolating atrial from ventricular electrical activity.
-
3The right atrium is composed of which three morphologically distinct components?
- AThe trabeculated appendage, the smooth-walled sinus venosus, and the anterior vestibule
- BThe crista terminalis, the fossa ovalis, and the coronary sinus
- CThe tendon of Todaro, the AV node, and the His bundle
- DThe SVC, IVC, and coronary sinus ostia only
Correct answer: A — The trabeculated appendage, the smooth-walled sinus venosus, and the anterior vestibule
The right atrium's macro-anatomy comprises the trabeculated right atrial appendage, the smooth-walled sinus venosus, and the anterior vestibule surrounding the tricuspid orifice.
-
4The base of the Triangle of Koch is formed by which structure?
- AThe tendon of Todaro
- BThe septal leaflet of the tricuspid valve
- CThe coronary sinus ostium
- DThe membranous septum
Correct answer: C — The coronary sinus ostium
The ostium of the coronary sinus forms the base of the triangle. The other two borders are the tendon of Todaro and the septal leaflet attachment of the tricuspid valve; the apex, where those two converge, overlies the membranous septum and marks where the His bundle penetrates. The compact AV node sits within the triangle — which is why it is the landmark for avoiding AV block during slow-pathway ablation.
-
5The sinoatrial node is located at which anatomical junction?
- AThe junction of the left atrium and the pulmonary veins
- BThe junction of the right atrium and the coronary sinus
- CThe junction of the right atrium and the superior vena cava
- DThe apex of the Triangle of Koch
Correct answer: C — The junction of the right atrium and the superior vena cava
The SA node is located anterolaterally at the junction of the right atrium and the superior vena cava, acting as the primary cardiac pacemaker.
ECG & rhythm foundations
-
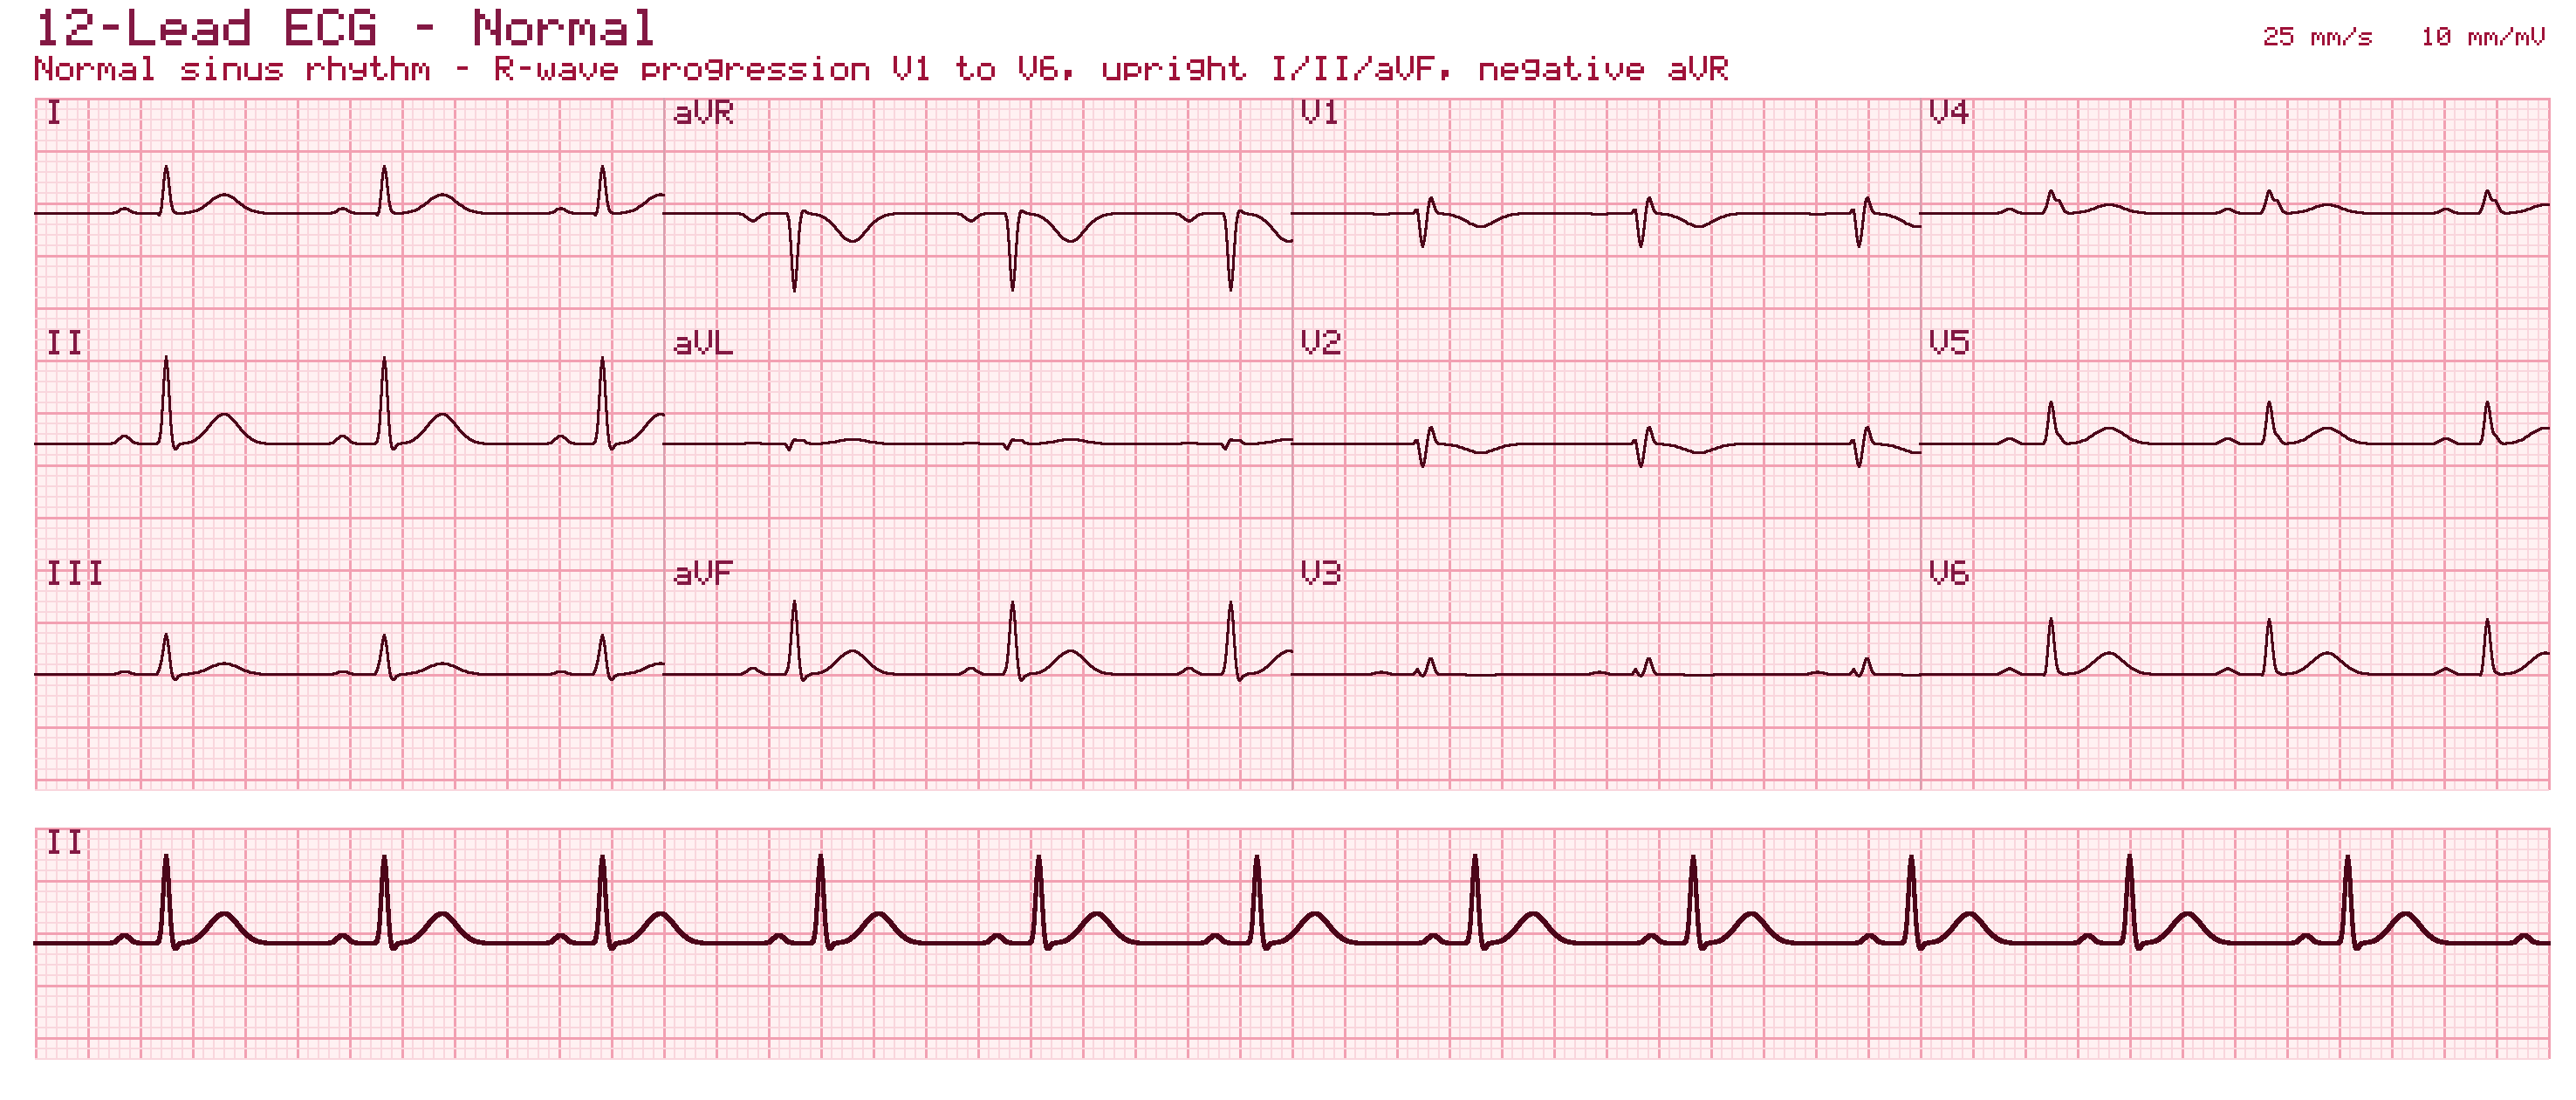
6On a 12-lead ECG, the P wave represents which electrophysiologic event?
- AAtrial depolarization
- BVentricular depolarization
- CVentricular repolarization
- DAV nodal conduction delay alone
Correct answer: A — Atrial depolarization
The P wave represents atrial depolarization, the QRS complex represents ventricular depolarization, and the T wave represents ventricular repolarization.
-
7Normal sinus rhythm is characterized by which combination of findings?
- AAn irregularly irregular rhythm with no discrete P waves
- BA P wave before every QRS with a consistent PR interval and a regular rate of 60-100 bpm
- CA regular sawtooth pattern with a 2:1 conduction ratio
- DComplete dissociation between P waves and QRS complexes
Correct answer: B — A P wave before every QRS with a consistent PR interval and a regular rate of 60-100 bpm
Normal sinus rhythm shows a P wave before every QRS with a consistent PR interval and a regular rate of 60-100 bpm.
-
8ST elevation in leads II, III, and aVF localizes ischemia to which coronary territory?
- AThe anterior/septal wall, typically LAD territory
- BThe lateral wall, typically circumflex territory
- CThe inferior wall, typically RCA territory
- DThe posterior wall exclusively
Correct answer: C — The inferior wall, typically RCA territory
ST elevation in II, III, and aVF localizes to the inferior wall, typically supplied by the RCA.
-
9The classic WPW/pre-excitation ECG pattern consists of a short PR interval combined with which additional finding?
- AA prolonged QT interval with no PR change
- BA regular sawtooth flutter wave pattern
- CA slurred initial upstroke of the QRS (a delta wave)
- DProgressive PR interval lengthening
Correct answer: C — A slurred initial upstroke of the QRS (a delta wave)
The classic WPW pattern is a short PR interval combined with a slurred initial upstroke of the QRS, the delta wave, reflecting the fusion of accessory pathway and normal conduction wavefronts.
-
10During baseline intracardiac measurements, which interval specifically represents the conduction time through the specialized His-Purkinje system?
- AAH Interval
- BHis Duration (H)
- CHV Interval
- DPA Interval
Correct answer: C — HV Interval
The HV interval represents conduction time through the specialized His-Purkinje system, whereas the PA and AH intervals measure intra-atrial and AV nodal conduction times, respectively.
The diagnostic EP study & pacing protocols
-
11The effective refractory period (ERP) of cardiac tissue is defined as which interval?
- AThe time from stimulus to the onset of the QRS complex
- BThe interval between the S1 drive train and the S2 extrastimulus
- CThe interval during which a stimulus cannot produce a propagated response
- DThe interval between two consecutive P waves
Correct answer: C — The interval during which a stimulus cannot produce a propagated response
The effective refractory period is the interval during which a stimulus cannot produce a propagated response.
-
12A diagnostic stimulator such as the Micropace EPS320 delivers pulses within approximately what current range?
- A50 to 200 mA
- B500 to 1000 mA
- C0.1 to 25 mA
- D1 to 5 A
Correct answer: C — 0.1 to 25 mA
Diagnostic stimulators deliver pulses ranging from approximately 0.1 to 25 mA, with durations of 0.5 to 10 ms.
-
13When executing a pacing protocol to measure the Sinus Node Recovery Time (SNRT), how long should the continuous pacing drive train be delivered at each fixed cycle length?
- A60 to 90 seconds
- B30 to 40 seconds
- C15 to 20 seconds
- D5 to 10 seconds
Correct answer: B — 30 to 40 seconds
Evaluating sinus node automaticity via the SNRT protocol requires pacing the high right atrium at fixed cycle lengths for 30 to 40 seconds before cessation.
-
14When assessing the returning signal sequence upon cessation of rapid ventricular pacing, a response pattern of 'A-A-V' (Atrium-Atrium-Ventricle) dictates which specific diagnosis?
- AAtrial Tachycardia
- BVentricular Tachycardia
- CAVNRT
- DOrthodromic AVRT
Correct answer: A — Atrial Tachycardia
An 'A-A-V' response definitively diagnoses an atrial tachycardia because the extra atrial signal demonstrates the presence of an independent focal driver in the atria rather than an AV nodal reentrant loop.
-
15In pace mapping, a 12/12 match between the paced 12-lead ECG morphology and the clinical tachycardia template suggests which finding?
- AThe catheter is definitively not near the arrhythmogenic focus
- BThe catheter is located at the arrhythmogenic origin
- CThe tachycardia is definitely not reentrant in mechanism
- DNo further mapping or ablation is required regardless of hemodynamics
Correct answer: B — The catheter is located at the arrhythmogenic origin
A 12/12 match between the paced morphology and the clinical tachycardia template on pace mapping suggests the catheter is at the arrhythmogenic origin of a focal tachycardia or the exit site of a macro-reentrant circuit.
Access, ablation & 3D mapping
-
16The right internal jugular vein is generally preferred over the left for central venous access because it provides which advantage?
- AA direct, straight route to the superior vena cava
- BA lower risk of carotid artery puncture in all patients
- CThe only route that avoids fluoroscopy
- DDirect continuity with the coronary sinus
Correct answer: A — A direct, straight route to the superior vena cava
The right internal jugular vein provides a direct, straight route to the superior vena cava, whereas the left IJ takes a sharp turn often requiring fluoroscopy for safe placement.
-
17The cephalic vein cutdown for lead access is favored over subclavian puncture primarily because it avoids which risk?
- ALead insulation breach
- BPhrenic nerve stimulation
- CSubclavian crush syndrome and pneumothorax
- DTricuspid valve interference
Correct answer: C — Subclavian crush syndrome and pneumothorax
The cephalic vein cutdown prevents subclavian crush syndrome (lead compression between the clavicle and first rib) and entirely negates the risk of pneumothorax.
-
18The critical, slow-conduction zone targeted for ablation in typical atrial flutter is located where?
- AThe cavo-tricuspid isthmus
- BThe His bundle
- CThe fossa ovalis
- DThe pulmonary vein antra
Correct answer: A — The cavo-tricuspid isthmus
The cavo-tricuspid isthmus, the tissue between the inferior vena cava and the tricuspid annulus, is the critical slow-conduction zone and ablation target in typical CTI-dependent atrial flutter.
-
19Following PFA for pulmonary vein isolation, entrance block is confirmed by which finding?
- AA shortened HV interval
- BCapture of the left atrial appendage during high-output pacing
- CAbsence of intrinsic pulmonary vein potentials on the multipolar PFA catheter
- DElevated lead impedance
Correct answer: C — Absence of intrinsic pulmonary vein potentials on the multipolar PFA catheter
Entrance block is confirmed by the absence of intrinsic PV potentials recorded on the multipolar PFA catheter, confirming signals from the left atrium can no longer enter the vein.
-
20Compared with traditional fluoroscopy, 3D electroanatomical mapping systems provide which additional capability?
- AIntegration of spatial localization with intracardiac electrograms for voltage and activation maps
- BAutomatic defibrillation capability
- CDirect measurement of coronary flow reserve
- DElimination of the need for any catheter
Correct answer: A — Integration of spatial localization with intracardiac electrograms for voltage and activation maps
Unlike fluoroscopy, which offers only 2D shadows with no electrical information, 3D EAM systems integrate spatial localization with intracardiac electrograms to create anatomical, voltage, and activation maps.
Devices: pacemakers, ICDs & CRT
-
21While diagnostic EP studies identify arrhythmia substrates, Cardiac Rhythm Management (CRM) devices such as pacemakers and ICDs provide which type of intervention?
- ALong-term therapeutic intervention
- BA one-time diagnostic snapshot with no ongoing function
- CPurely investigational, non-therapeutic monitoring
- DShort-term intervention lasting only 24-48 hours
Correct answer: A — Long-term therapeutic intervention
While diagnostic EP identifies arrhythmia substrates, CRM devices provide long-term therapeutic intervention through ongoing pacing or defibrillation capability.
-
22An ICD lead includes a pace/sense electrode plus which additional component not found on a standard pacemaker lead?
- AOne or two high-voltage shock coils
- BAn additional atrial sensing ring only
- CA drug-eluting polymer coating
- DA dedicated MRI-safety chip
Correct answer: A — One or two high-voltage shock coils
An ICD lead includes a pace/sense electrode similar to a pacemaker lead, plus one or two high-voltage shock coils that allow delivery of a defibrillation shock.
-
23Detected ventricular arrhythmias in a modern ICD are typically classified into how many therapy zones, with different response algorithms?
- ATwo zones -- typically a slower VT zone and a faster VF zone
- BA single unified zone for all ventricular arrhythmias
- CFive distinct zones for every possible heart rate
- DZones are not used; therapy is purely rate-independent
Correct answer: A — Two zones -- typically a slower VT zone and a faster VF zone
Detected ventricular arrhythmias are typically classified into a slower VT zone and a faster VF zone, each with a different programmed response algorithm.
-
24CRT is fundamentally a therapy targeted at correcting which underlying physiological problem?
- AIsolated valvular stenosis with no conduction abnormality
- BElectrical and resulting mechanical dyssynchrony between the ventricles
- CIsolated coronary artery stenosis with normal conduction
- DIsolated atrial fibrillation with normal ventricular EF
Correct answer: B — Electrical and resulting mechanical dyssynchrony between the ventricles
CRT is fundamentally targeted at correcting electrical dyssynchrony (and the resulting mechanical dyssynchrony) between the ventricles, most classically from a wide LBBB pattern.
-
25Beyond lead fracture/insulation failure and myopotential oversensing, which additional source of oversensing is described?
- AExternal electromagnetic interference (EMI)
- BIsolated patient anxiety with no electrical correlate
- CExcessive dietary caffeine intake
- DNormal T-wave morphology in a structurally normal heart
Correct answer: A — External electromagnetic interference (EMI)
External electromagnetic interference is described as an additional source of oversensing, each with characteristic signal patterns on interrogation that help localize the cause.
Bonus questions · week of Oct 12, 2026
-
26The Triangle of Koch, which houses the AV node at its apex, is bounded by which three structures?
- AThe SVC, the IVC, and the eustachian ridge
- BThe fossa ovalis, the mitral annulus, and the crista terminalis
- CThe His bundle, the right bundle branch, and the moderator band
- DThe tendon of Todaro, the coronary sinus ostium, and the tricuspid annulus
Correct answer: D — The tendon of Todaro, the coronary sinus ostium, and the tricuspid annulus
The Triangle of Koch is bounded posteriorly by the tendon of Todaro, inferiorly by the coronary sinus ostium, and anteriorly by the tricuspid annulus, housing the AV node at its apex.
Bonus questions · week of Oct 19, 2026
-
27The sinoatrial node is located at which anatomical landmark?
- AThe apex of the Triangle of Koch
- BThe epicardial sulcus terminalis at the superior cavoatrial junction
- CThe central fibrous body
- DThe membranous septum
Correct answer: B — The epicardial sulcus terminalis at the superior cavoatrial junction
The SA node is located in the epicardial sulcus terminalis at the superior cavoatrial junction, distinct from the AV node's location at the apex of the Triangle of Koch.
Bonus questions · week of Oct 26, 2026
-
28The AV node's dual conduction pathways (fast and slow) form the anatomical substrate for which arrhythmia?
- AAtrial fibrillation
- BVentricular fibrillation
- CAV nodal reentrant tachycardia (AVNRT)
- DSinus node dysfunction
Correct answer: C — AV nodal reentrant tachycardia (AVNRT)
The AV node's dual fast and slow conduction pathways form the anatomical substrate for AVNRT, the most common regular narrow-complex SVT.
-
29When a transvenous ICD detects a rapid ventricular rate in the programmed VT detection zone, the FIRST therapy it typically delivers (before a shock) is:
- AAsynchronous defibrillation at maximum output
- BAntitachycardia pacing (ATP)
- CRate-adaptive pacing at 60 bpm
- DSynchronized cardioversion at 100 J
Correct answer: B — Antitachycardia pacing (ATP)
Antitachycardia pacing (ATP) is delivered first in most programmed VT zones. ATP delivers a burst of rapid pacing stimuli that attempt to enter and terminate the reentrant VT circuit without a shock. ATP terminates the majority of monomorphic VTs and avoids patient discomfort. Shocks are reserved for ATP failure or for VF zone detections.
-
30The HV interval measures conduction time through which specialized system, and normally falls within what range?
- AThe AV node, 55-125 ms
- BThe sinus node, 25-55 ms
- CThe coronary venous system, 100-200 ms
- DThe His-Purkinje system, 35-55 ms
Correct answer: D — The His-Purkinje system, 35-55 ms
The HV interval measures conduction time through the His-Purkinje system and normally falls within 35-55 ms.
-
31Which ion channel current is responsible for the phase 4 spontaneous diastolic depolarization in pacemaker cells?
- AThe inward rectifier potassium current (IK1)
- BThe rapid delayed rectifier potassium current (IKr)
- CThe funny current (If)
- DThe fast sodium current (INa)
Correct answer: C — The funny current (If)
The funny current (If), conducted by HCN channels, is the primary driver of spontaneous diastolic depolarization in sinoatrial nodal cells.
Bonus questions · week of Nov 2, 2026
-
32A dual-coil ICD lead configuration places high-voltage shock coils in which two locations?
- AThe right ventricle and the superior vena cava
- BThe coronary sinus and the right ventricle
- CThe left ventricle and the right atrium
- DThe right atrium and the right ventricle
Correct answer: A — The right ventricle and the superior vena cava
A dual-coil ICD lead positions one high-voltage shock coil in the right ventricle and a second in the superior vena cava, allowing shock delivery across the coil-to-coil or coil-to-can pathway.
-
33The AH interval is highly sensitive to which physiologic influence?
- ABody temperature
- BAutonomic tone
- CHemoglobin concentration
- DRespiratory rate
Correct answer: B — Autonomic tone
The AH interval (approximately 55-125 ms) denotes AV nodal conduction time, which is highly susceptible to autonomic tone and decremental delay.
-
34During electroanatomical mapping, what tissue characteristic corresponds to a bipolar voltage amplitude of less than 0.5 mV?
- ADiseased tissue indicating border zones
- BHealthy myocardium capable of rapid conduction
- CDense scar tissue that is electrically nonconductive
- DThe compact His bundle
Correct answer: C — Dense scar tissue that is electrically nonconductive
A voltage amplitude of less than 0.5 mV identifies dense scar tissue that acts as an anatomical barrier anchoring reentrant circuits, whereas voltages above 0.5 mV indicate either diseased or healthy myocardium.
Bonus questions · week of Nov 9, 2026
-
35Secondary prevention ICD implantation is indicated after which clinical event?
- AA documented sustained ventricular arrhythmia or cardiac arrest not attributable to a fully reversible cause
- BAn asymptomatic EF of 40% found incidentally on echocardiography
- CA single isolated PVC on routine monitoring
- DA first-degree AV block found on a screening ECG
Correct answer: A — A documented sustained ventricular arrhythmia or cardiac arrest not attributable to a fully reversible cause
Secondary prevention ICDs are implanted after a documented sustained ventricular arrhythmia or cardiac arrest not attributable to a fully reversible cause, since these patients have already demonstrated their arrhythmic risk directly.
-
36Prolongation of the HV interval beyond the normal range most strongly suggests which finding?
- AIsolated sinus node dysfunction
- BInfranodal (His-Purkinje) conduction disease that may necessitate permanent pacing
- CAn accessory pathway bypassing the AV node
- DNormal AV nodal decremental conduction
Correct answer: B — Infranodal (His-Purkinje) conduction disease that may necessitate permanent pacing
The HV interval (35-55 ms) measures His-Purkinje conduction time; prolongation suggests infranodal disease that may necessitate permanent pacing.
-
37The sinoatrial node, the heart's primary pacemaker, is located at which anatomical junction?
- AThe apex of the Triangle of Koch
- BThe junction of the coronary sinus and left atrium
- CThe membranous interventricular septum
- DThe junction of the right atrium and the superior vena cava, positioned anterolaterally
Correct answer: D — The junction of the right atrium and the superior vena cava, positioned anterolaterally
The SA node is located anterolaterally at the junction of the right atrium and superior vena cava, acting as the heart's primary pacemaker.
Bonus questions · week of Nov 16, 2026
-
38The Triangle of Koch, which houses the AV node at its apex, is bounded by which three structures?
- AThe tendon of Todaro, the coronary sinus ostium, and the tricuspid annulus
- BThe SVC, the IVC, and the eustachian ridge
- CThe fossa ovalis, the mitral annulus, and the crista terminalis
- DThe His bundle, the right bundle branch, and the moderator band
Correct answer: A — The tendon of Todaro, the coronary sinus ostium, and the tricuspid annulus
The Triangle of Koch is bounded posteriorly by the tendon of Todaro, inferiorly by the coronary sinus ostium, and anteriorly by the tricuspid annulus, housing the AV node at its apex.
-
39How does parasympathetic muscarinic stimulation affect SA nodal automaticity?
- AIt has no measurable effect on pacemaker rate
- BIt converts the SA node to a fast-response action potential
- CIt increases the slope of phase 4 depolarization, accelerating the pacemaker rate
- DIt decreases the slope of phase 4 diastolic depolarization, slowing the pacemaker rate
Correct answer: D — It decreases the slope of phase 4 diastolic depolarization, slowing the pacemaker rate
Parasympathetic muscarinic stimulation decreases the slope of phase 4 diastolic depolarization, slowing the sinus rate -- the opposite effect of sympathetic stimulation.
-
40The shock coil of a transvenous ICD lead is typically positioned in which location to maximize defibrillation efficacy?
- AThe coronary sinus
- BThe left ventricular epicardium
- CThe right ventricular apex or septum
- DThe superior vena cava only
Correct answer: C — The right ventricular apex or septum
The active shock coil of a transvenous ICD lead is positioned in the right ventricle (apex or mid-septum). Many leads also have a proximal coil in the SVC or right atrium. The defibrillation vector is from the RV coil to the ICD can (and proximal coil if present), creating a current path that spans the ventricular myocardium.
Practice the whole blueprint with Cardiac Codex
These are a taste. The app has 2,198 practice questions with explanations, two full-length blueprint-matched RCES mock exams, live and timed, flashcards, mastery tracking that targets your weak domains, and Cardiac Coach — an AI tutor grounded in the curriculum you can ask from any lesson or missed question.
Start free Read the RCES exam guide →Keep going
About these free RCES questions
Are these RCES practice questions really free?
Yes. All the questions on this page, including the weekly bonus questions, are free to use with no signup or payment. They are a sample of the practice bank inside the Cardiac Codex app.
Are these the actual questions from the RCES exam?
No. These are original questions written to the CCI RCES electrophysiology blueprint. Real exam items are secured by Cardiovascular Credentialing International and are never reproduced. Practicing blueprint-matched questions is the legitimate way to prepare.
What topics do these RCES questions cover?
They mirror the EP blueprint: conduction-system anatomy, ECG and rhythm interpretation, the diagnostic EP study and pacing protocols, catheter ablation and 3D electroanatomical mapping, and cardiac rhythm management devices — pacemakers, ICDs, and CRT.
Where can I get more RCES practice questions?
The Cardiac Codex app pairs its practice bank with a curriculum-grounded AI tutor, and two full-length, blueprint-matched RCES mock exams, live and timed. You can also take a free 25-question RCES diagnostic that scores you by topic.